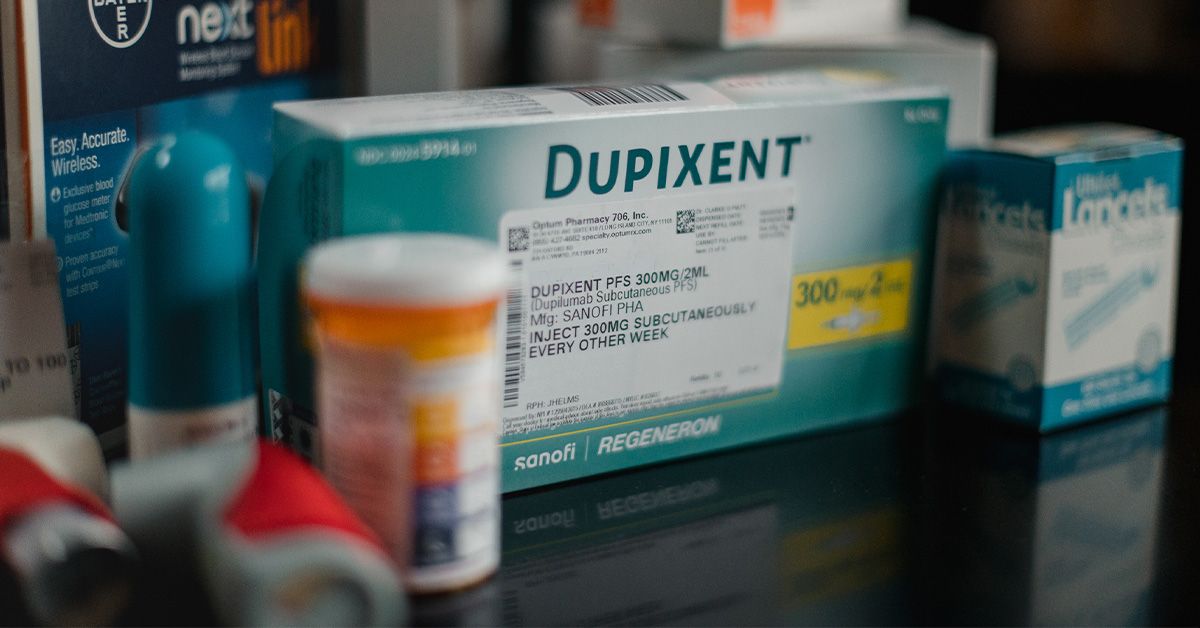
Note: The medication is correctly spelled Dupixent, not “Dupxient.” This article keeps the requested title wording for search intent, but uses the approved drug name throughout the content. This information is educational and should not replace advice from a licensed healthcare professional.
Introduction: When Swallowing Feels Like a Strategy Game
Eosinophilic esophagitis, often shortened to EoE, is not just “bad reflux with a fancy name.” It is a chronic immune-driven condition that causes inflammation in the esophagus, the tube that carries food from your mouth to your stomach. For many people, EoE turns ordinary meals into a slow-motion negotiation: chew carefully, drink water, avoid problem foods, and hope dinner does not stage a dramatic comeback. Symptoms can include difficulty swallowing, food getting stuck, regurgitation, belly pain, nausea, vomiting, and chest discomfort. Food impaction can become urgent and may require emergency care.
Dupixent, also known by its generic name dupilumab, is a biologic medication approved in the United States for EoE in adults and children aged 1 year and older who weigh at least 15 kg. It is not a quick antacid, not a rescue medicine, and not a magic “eat anything tomorrow” ticket. It works by calming specific immune signals involved in type 2 inflammation, which is a major driver of EoE in many patients.
What Is Dupixent for EoE?
Dupixent is an injectable monoclonal antibody. In everyday language, that means it is a targeted medicine designed to block certain immune pathways rather than broadly suppressing the entire immune system. For EoE, Dupixent is used to reduce inflammation inside the esophagus, improve swallowing symptoms, and help lower eosinophil activity seen on biopsy.
The FDA first approved Dupixent for EoE in 2022 for patients aged 12 years and older who weighed at least 40 kg. In January 2024, approval expanded to include children aged 1 to 11 years who weigh at least 15 kg, making it an important option for younger pediatric patients with EoE.
How Dupixent Works for EoE
The Immune System Is the Main Character
EoE is strongly linked with allergic and type 2 inflammatory pathways. In many patients, immune signals attract eosinophils into the esophageal lining. Eosinophils are white blood cells that can be helpful in the right setting, but in EoE they gather where they should not and contribute to swelling, irritation, tissue changes, and swallowing problems.
Dupixent blocks the interleukin-4 receptor alpha subunit, which affects signaling from two key inflammatory cytokines: IL-4 and IL-13. These cytokines help drive type 2 inflammation. By interfering with that signaling, Dupixent can reduce inflammatory activity connected to EoE. The prescribing information notes that blocking IL-4R alpha inhibits IL-4 and IL-13 cytokine-induced inflammatory responses, although the exact mechanism in every condition is not fully established.
Why That Matters in Real Life
For patients, the goal is not just prettier biopsy numbers. The goal is eating with less fear, fewer swallowing episodes, less food sticking, and better long-term control of esophageal inflammation. EoE can lead to narrowing or scarring over time, so treatment is often about both symptom relief and prevention of future complications.
How Long Does It Take to Receive Dupixent?
The answer depends on three big checkpoints: prescription, insurance approval, and specialty pharmacy delivery. Dupixent is usually handled through a specialty pharmacy, not picked up casually like a bottle of cough drops. After a clinician prescribes it, insurance may approve it right away, request more information, or deny it and require an appeal. Once approved, the specialty pharmacy contacts the patient or caregiver to schedule shipment. The medication cannot be delivered until that delivery is arranged.
A Realistic Timeline
Some patients may receive Dupixent within several days after approval, while others may wait a few weeks or longer if prior authorization, missing paperwork, insurance appeals, copay assistance, or pharmacy coordination slows things down. The first shipment is often the slowest because the system has to confirm coverage, benefits, delivery address, storage instructions, and training needs.
The Common Steps Before the First Dose Arrives
- Step 1: Your gastroenterologist, allergist, or other prescriber confirms EoE diagnosis and treatment plan.
- Step 2: The prescription is sent to a specialty pharmacy or support program.
- Step 3: Insurance reviews the request, often through prior authorization.
- Step 4: The specialty pharmacy calls to confirm details and schedule delivery.
- Step 5: The medication is shipped to your home or healthcare office, depending on the plan.
- Step 6: Injection training may be provided before at-home administration.
Dupixent Dosage for EoE: What the Label Says
For EoE, dosing is based on body weight. According to the current prescribing information, patients aged 1 year and older weighing 15 kg to less than 30 kg receive 200 mg every 2 weeks; those weighing 30 kg to less than 40 kg receive 300 mg every 2 weeks; and those weighing 40 kg or more receive 300 mg every week. A prescriber should decide the correct dose and schedule for each patient.
How Long Until Dupixent Starts Working?
Dupixent is not designed to work like an instant heartburn tablet. EoE improvement is usually measured over weeks to months. In clinical studies, improvement was commonly evaluated at Week 24, with longer follow-up at Week 52. Manufacturer-reported EoE trial data showed reductions in dysphagia symptom scores at Week 24 and continued improvement in some patients through Week 52.
Histologic improvement means the esophageal biopsy shows fewer eosinophils. In EoE studies, Dupixent demonstrated higher rates of histologic remission compared with placebo at Week 24. For example, one reported trial section showed histologic remission in 60% of Dupixent-treated patients versus 5% with placebo in Part A at Week 24; another section reported 59% with Dupixent versus 6% with placebo in Part B.
Who Might Be Considered for Dupixent?
Dupixent may be considered for patients with confirmed EoE, especially when symptoms or inflammation remain active despite other therapies, or when a patient also has other type 2 inflammatory conditions such as asthma, eczema, or chronic rhinosinusitis with nasal polyps. Updated American College of Gastroenterology guidance describes dupilumab as an option for patients who are resistant to initial therapies and for those with multiple atopic conditions.
That does not mean every EoE patient starts with Dupixent. Many treatment plans begin with proton pump inhibitors, swallowed topical steroids, or dietary elimination strategies. Some patients also need esophageal dilation if narrowing is present. EoE care is usually personalized because symptoms, biopsy findings, allergies, age, food restrictions, and lifestyle all matter.
Benefits Patients May Notice
Better Swallowing
The most meaningful improvement for many patients is less dysphagia, which means less trouble swallowing. Someone who used to avoid steak, bread, rice, or dry chicken may gradually feel more confident eating normal textures again. That does not mean reckless eating is wise; it means meals may feel less like a tactical mission.
Less Inflammation on Biopsy
Doctors do not rely only on “I feel better” because EoE can remain active even when symptoms improve. Endoscopy and biopsy are commonly used to assess response. The ACG notes that response to diet therapy should be assessed with endoscopy and biopsy rather than symptoms alone, and the same principle is often important in EoE monitoring overall.
Possible Long-Term Control
EoE is chronic, so long-term control matters. A therapy that reduces inflammation may help limit future narrowing, scarring, and food impaction risk. Still, treatment decisions should be made with a clinician because long-term plans depend on response, side effects, access, and patient preference.
Possible Side Effects and Safety Considerations
Common side effects listed for Dupixent include injection site reactions, upper respiratory tract infections, eye and eyelid inflammation, herpes virus infections, common cold symptoms, eosinophilia, dizziness, muscle pain, diarrhea, and throat pain. Serious allergic reactions can occur. Patients should contact a healthcare professional if they develop concerning symptoms such as swelling, breathing trouble, severe rash, eye pain, vision changes, or worsening joint symptoms.
Dupixent is not used for sudden choking, acute food impaction, or emergency breathing problems. If food is stuck and will not pass, or if there is trouble breathing, severe chest pain, or inability to swallow saliva, urgent medical care is needed. Food impaction can be a medical emergency.
How to Prepare While Waiting for Dupixent
Waiting for a specialty medication can feel like watching a loading screen with no progress bar. While the prescription is moving through insurance and pharmacy systems, patients can keep a symptom diary, track foods that trigger swallowing problems, write down questions for the prescriber, and answer unknown pharmacy phone calls. Missing the specialty pharmacy call can delay delivery, which is annoying in the same way losing your keys while already late is annoying.
Helpful Questions to Ask the Care Team
- How will we measure whether Dupixent is working?
- When should follow-up endoscopy or biopsy be considered?
- Should current EoE medicines or diet changes continue after starting Dupixent?
- What side effects should be reported immediately?
- Who teaches injection technique?
- What should I do if a dose is missed?
- Who handles insurance appeals if the first request is denied?
Dupixent vs. Other EoE Treatments
EoE treatment is not one-size-fits-all. Proton pump inhibitors may help some patients, especially when reflux-like symptoms overlap with EoE. Swallowed topical steroids target esophageal inflammation and are commonly used. Elimination diets can work well but may be difficult socially and nutritionally without dietitian support. Dilation can help when the esophagus is narrowed, but it treats narrowing rather than the underlying inflammation.
Dupixent is different because it targets immune signaling upstream. It may be especially attractive when EoE is severe, persistent, or accompanied by other allergic conditions. However, it is injectable, expensive without coverage, and often requires specialty pharmacy coordination. In plain English: the science is elegant, but the paperwork may still wear clunky shoes.
Experience Section: What Starting Dupixent for EoE Can Feel Like
Many patients describe the beginning of Dupixent treatment as two separate journeys: the medical journey and the administrative obstacle course. The medical part may feel hopeful. After years of chewing slowly, avoiding certain foods, or pretending not to worry during restaurant meals, finally having a targeted EoE medication can feel like someone turned on a light in a very confusing room.
The administrative part can be less glamorous. A patient may leave the doctor’s office thinking, “Great, I’m starting Dupixent,” only to learn that the medication still has to pass through insurance review, prior authorization, specialty pharmacy setup, and delivery scheduling. This is normal for many biologic medications. It does not necessarily mean something is wrong. It means the system has several gates, and each gate has a clipboard.
Once the specialty pharmacy calls, things usually feel more real. Patients may be asked to confirm address, insurance details, copay information, allergies, storage understanding, and delivery timing. Because Dupixent requires careful handling, the shipment needs to be scheduled. This is why saving the pharmacy number matters. Letting unknown calls go to voicemail for a week can delay the first box from arriving.
The first injection can bring mixed emotions. Some people are nervous about needles; others are simply relieved to begin. Training helps. Caregivers of children may feel extra pressure, especially if the child already has anxiety around food, medical visits, or swallowing. A calm routine can help: choose a consistent day, prepare supplies, follow the instructions from the care team, and avoid turning injection time into a household drama production.
Symptom tracking is one of the most useful habits after starting. Instead of relying on vague impressions like “I think sandwiches are less scary now,” patients can record swallowing episodes, avoided foods, mealtime anxiety, chest discomfort, regurgitation, and any side effects. This gives the doctor better information at follow-up. It also helps patients notice progress that may happen gradually rather than all at once.
Some patients may feel better before the next endoscopy confirms improvement. Others may need more time. Because EoE symptoms and biopsy results do not always move perfectly together, follow-up testing matters. A patient might feel better but still have inflammation, or feel only modest symptom improvement while tissue healing is underway. That is why EoE care works best as a partnership between symptoms, scopes, biopsies, and practical quality-of-life goals.
The emotional side is real too. People with EoE often build habits around fear: tiny bites, endless water, avoiding social meals, or scanning menus like a detective. If Dupixent helps, regaining confidence with food can feel surprisingly emotional. The win is not always dramatic. Sometimes it is simply eating lunch without planning an escape route. And honestly, that is a pretty excellent win.
Conclusion: Dupixent for EoE Is Targeted, Promising, and Not Instant
Dupixent for EoE works by targeting immune signals involved in type 2 inflammation, especially IL-4 and IL-13 pathways. It is approved for adults and children aged 1 year and older who weigh at least 15 kg, with dosing based on body weight. The time to receive Dupixent varies because the prescription usually moves through insurance approval and specialty pharmacy delivery before the first dose arrives. Some patients may receive it quickly after approval; others may wait longer if prior authorization or appeals are needed.
For results, patience matters. Clinical improvement is often assessed over weeks to months, and trial data commonly focus on Week 24 and Week 52 outcomes. The best plan is to work closely with a gastroenterologist, allergist, pediatric specialist, or other qualified clinician, track symptoms carefully, keep follow-up appointments, and treat EoE as the chronic condition it is. Dupixent may not make EoE vanish overnight, but for the right patient, it can be a major step toward calmer meals, better swallowing, and fewer food-related plot twists.
Publishing note: This article is for general educational use only. Readers should consult a licensed healthcare professional for diagnosis, treatment decisions, dosing, side-effect concerns, and emergency symptoms.

