Note: This is an original, web-ready article inspired by real information about the Yale System of Medical Education, trauma surgery training, and long-term professional growth in medicine.
Twenty years is a strange amount of time in medicine. It is long enough for a medical student to become an attending physician, long enough for the pager to be replaced by smartphones, and long enough for a young doctor who once panicked over anatomy to become the person calmly leading a trauma resuscitation at 2:17 a.m. It is also long enough to look back and ask a dangerous question: Did medical school shape the doctor, or did the doctor simply survive it?
For a trauma surgeon reflecting on the Yale System two decades later, the answer is not a neat little graduation-card slogan. The Yale System is not merely a quirky academic policy with fewer grades and more freedom. It is a philosophy. It assumes medical students are adults. It trades constant ranking for responsibility. It asks students to learn because patients will someday depend on what they know, not because a red number on a test says they are temporarily acceptable.
That sounds noble. It also sounds terrifying. Freedom, as every medical student eventually discovers, is not the same as vacation. At Yale School of Medicine, the absence of traditional grades and class rank does not mean the absence of pressure. It means the pressure moves inward. The competition is no longer against the person sitting beside you in lecture. It is against your own confusion, procrastination, ego, and, occasionally, the seductive belief that coffee can replace sleep, planning, and basic human judgment.
What Is the Yale System?
The Yale System of Medical Education dates back to the 1920s, when Dean Milton C. Winternitz helped reshape Yale School of Medicine around a radical idea: medical students should be treated as mature, self-directed learners. Instead of relying heavily on grades, class rankings, and rigid daily assignments, the school emphasized intellectual independence, scientific inquiry, formative feedback, and collaboration.
In the modern Yale MD program, the pre-clerkship period still reflects that spirit. There are no course grades and no class ranking during the first eighteen months, and the school places major emphasis on small-group learning, clinical reasoning, direct feedback, and anonymous examinations meant to help students assess progress rather than crush their souls into academically polished dust.
The model also includes a strong research tradition. Yale medical students are expected to engage in research and complete an MD thesis, a requirement rooted in the belief that physicians should not simply memorize what is known. They should learn how knowledge is created, challenged, revised, and sometimes thrown out like expired yogurt in the call-room refrigerator.
Why the Yale System Feels Different
Most high-achieving premedical students arrive at medical school with a well-rehearsed playbook: study hard, score high, collect honors, repeat until someone hands you a white coat. The Yale System interrupts that rhythm. Without constant grades, the usual scoreboard disappears. For some students, that is liberating. For others, it is like being dropped in the woods with a compass, a library card, and a polite suggestion to become excellent.
That discomfort is part of the lesson. In clinical medicine, no one provides a syllabus for every emergency. A patient with multiple injuries does not arrive labeled “Chapter 7: Thoracic Trauma.” A trauma surgeon must identify priorities quickly, ask better questions, use available evidence, communicate clearly, and recognize what they do not yet know. The Yale System, at its best, trains the habits beneath the knowledge: curiosity, discipline, humility, and collaboration.
It also changes the social climate. When students are not fighting over class rank, helping a classmate no longer feels like giving away oxygen on a sinking submarine. A student who understands renal physiology can teach the student who does not. A classmate with a neuroscience background can explain a pathway without acting like the keeper of a sacred scroll. The result is not a magical utopia where everyone shares snacks and nobody panics. It is still medical school. But the incentives point toward teamwork rather than academic cage fighting.
The Trauma Surgeon’s Lens: Why Collaboration Matters
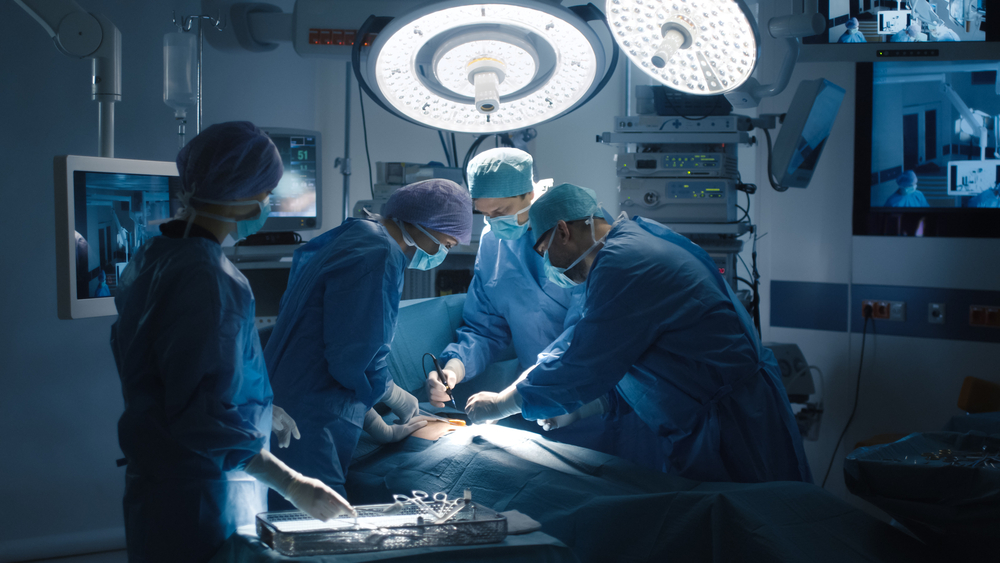
Trauma surgery is a team sport performed under the least relaxing conditions imaginable. When a badly injured patient arrives, the surgeon is not alone. Emergency physicians, anesthesiologists, nurses, respiratory therapists, radiology teams, blood bank staff, residents, students, and technicians all become part of a high-stakes choreography. Everyone has a job. Everyone needs the same mental map. Everyone must communicate without turning the room into a shouting contest with monitors.
The American College of Surgeons’ approach to trauma education, including Advanced Trauma Life Support, emphasizes organized assessment, prioritization, teamwork, and a common language for managing injured patients. That sounds very clinical, but underneath it is a human truth: no single doctor saves a trauma patient alone. The myth of the lone heroic surgeon makes good television. In the real trauma bay, it is usually a sign someone has watched too much television.
A medical education system that rewards collaboration prepares physicians for this reality. When a surgeon learns early to ask classmates for help, to offer help without keeping score, and to value shared understanding over personal ranking, that habit can follow them into residency and practice. In trauma care, pride is useful only in tiny doses. The best teams are not built around the loudest person in the room. They are built around trust, clarity, preparation, and the shared goal of getting the patient through the next five minutes.
The Hidden Challenge of No Grades
Critics of pass/fail or non-ranked systems often worry that students will study less without the pressure of grades. The fear is understandable. Many of us have met our own motivation and found it suspiciously fond of deadlines. But evidence from medical education has repeatedly suggested that pass/fail grading can reduce stress and burnout without necessarily damaging objective academic outcomes.
That does not mean pass/fail systems are effortless. In some ways, they demand more maturity. A grade can tell a student when to panic. A self-directed system requires students to notice earlier, reflect honestly, and seek help before disaster arrives wearing a little hat. The Yale System does not remove accountability. It changes the form of accountability from public comparison to private responsibility, faculty feedback, clinical performance, national exams, and long-term professional growth.
For a future trauma surgeon, that lesson is not theoretical. Surgeons live in a world where self-assessment is a survival skill. After a difficult case, you must ask what went well, what could have gone better, and what needs to change next time. You cannot wait for someone to hand you a letter grade after every operation. The operating room, like life, rarely distributes tidy report cards.
Humility: The Most Useful Thing Medical School Can Teach
Every medical student eventually meets the limits of raw intelligence. This usually happens around the time they realize the human body contains roughly nine million details and all of them seem testable, clinically relevant, or both. The student who was once the smartest person in every undergraduate classroom suddenly sits among classmates who are equally bright, deeply accomplished, and alarmingly comfortable using words like “pathophysiology” before breakfast.
The Yale System can intensify that moment because students cannot hide behind a simple ranking. If an anonymous exam goes poorly, the embarrassment may be private, but the lesson is personal. You must decide what to do next. You can pretend everything is fine. You can spiral. Or you can ask for help.
That actasking for helpmay be one of the most important transitions in medical training. It turns medicine from a performance into a profession. The best physicians are not the ones who never feel lost. They are the ones who notice when they are lost, pause, consult, study, and return better prepared. In trauma surgery, humility is not decorative. It keeps patients alive.
Learning for Patients, Not for Points
The deeper promise of the Yale System is that students learn to connect knowledge with responsibility. Anatomy is not just a course. It is the map you need when bleeding hides behind tissue. Physiology is not just a lecture series. It is the logic behind shock, resuscitation, ventilation, and organ failure. Communication is not just a soft skill. It is how teams avoid errors, how families receive devastating news, and how patients feel seen rather than processed.
When students learn only for exams, knowledge can become disposable. Memorize, perform, forget, repeat. The Yale philosophy pushes against that pattern by asking students to build durable habits of inquiry. The goal is not to win medical school. The goal is to become the kind of physician who can keep learning after medical school ends, because medicine will not politely freeze itself at graduation.
Twenty years later, that may be the most valuable lesson. A trauma surgeon’s work changes constantly. New imaging protocols emerge. Massive transfusion strategies evolve. Critical care practices shift. Artificial intelligence enters clinical conversations. Team communication becomes more structured. Patient expectations change. If a physician has not learned how to learn, the diploma ages faster than milk.
The Research Mindset and the MD Thesis
Yale’s thesis requirement is more than an academic ornament. It reflects a belief that physicians should understand research from the inside. Even doctors who never run a laboratory need to interpret evidence, recognize bias, evaluate claims, and understand why one study changes practice while another merely creates a dramatic headline and a busy week on medical Twitter.
For trauma surgeons, the research mindset is practical. Trauma care depends on systems, timing, protocols, outcomes data, and constant performance improvement. A surgeon who thinks scientifically can ask better questions: Are we activating the trauma team appropriately? Are blood products reaching the bedside fast enough? Are we preventing complications? Are our protocols helping rural transfer patients as well as urban walk-ins? Are we measuring what matters?
The Yale System’s emphasis on independent investigation helps students see medicine as a living discipline. Knowledge is not a marble statue. It is scaffolding. Every generation of physicians strengthens, repairs, and sometimes dismantles parts of it.
Freedom Is Not the Absence of Structure
A common misunderstanding of the Yale System is that it simply gives students freedom. In reality, effective freedom requires structure. Students need mentorship, feedback, learning goals, clinical exposure, and opportunities to test themselves. Yale’s current curriculum continues to evolve around these needs, including more competency-based approaches, interactive learning, and structured opportunities for students to measure progress.
This matters because independence without feedback can become drift. A student may feel busy without becoming better. A trainee may read endlessly but fail to apply knowledge. A physician may mistake confidence for competence, which is how medicine reminds us, usually with paperwork, that confidence is not a vital sign.
The strongest version of the Yale System is not “do whatever you want.” It is closer to “own your education, seek guidance, use feedback, help your peers, and remember that patients are the reason this matters.” That is a harder message than a syllabus. It is also a more durable one.
Why the Yale System Still Matters 20 Years Later
Medical education now faces pressures that earlier generations could barely imagine. Students must master expanding biomedical knowledge, navigate electronic health records, prepare for changing licensing exams, understand health systems, respond to burnout, and learn in a world where information is everywhere but wisdom remains stubbornly non-downloadable.
In that environment, the Yale System feels less like an old academic curiosity and more like an early warning from the future. It recognized that physicians need more than memorization. They need self-direction. They need collaboration. They need scientific habits of mind. They need feedback without humiliation. They need room to become not just test-takers but thinkers.
For a trauma surgeon, the proof appears in small moments. It appears when a resident speaks up about a missed detail. It appears when a nurse challenges an assumption and the team listens. It appears when an attending admits uncertainty, calls a colleague, and models professional humility. It appears when teaching becomes less about displaying knowledge and more about building capacity in others.
Twenty years after medical school, the memory that lasts may not be a lecture title or a lab practical. It may be the moment a classmate explained a concept without judgment. The moment failure became private data instead of public shame. The moment a student realized that medicine is not a race against peers, but a lifelong commitment to patients.
Additional Reflections From the Trauma Bay: Experience After the Yale System
In trauma surgery, the lessons of a collaborative medical education do not arrive as sentimental flashbacks. They arrive wearing gloves, standing beside a stretcher, and asking for decisions before the CT scanner is ready. The trauma bay is where theory becomes muscle memory. It is also where a physician learns that no educational philosophy is worth much unless it survives contact with fear, blood, noise, fatigue, and the deeply inconvenient fact that human beings do not follow textbook order.
One of the most important experiences related to the Yale System is learning how to function when no one is handing out grades. In the hospital, there is no dean standing at the foot of the bed announcing, “Excellent central line placement, honors-level empathy, minor deduction for coffee breath.” Instead, feedback comes through outcomes, team trust, patient recovery, complications, and the quiet internal review that happens after a case ends. A self-directed learner is better prepared for that world because the habit has already been built: assess yourself, seek feedback, improve, repeat.
Another experience is the realization that asking for help is not weakness. Early in training, many young doctors imagine competence as total independence. Later, especially in surgery, they learn that competence includes knowing when to call vascular surgery, when to involve interventional radiology, when to ask anesthesia for another set of eyes, and when to tell the family the truth with compassion instead of hiding behind medical fog. The Yale System’s collaborative culture can make that humility feel normal rather than embarrassing.
Teaching residents and students also changes the meaning of the Yale System. A trauma surgeon who once benefited from classmates’ generosity may become the attending who creates psychological safety in a chaotic room. That does not mean lowering standards. Trauma surgery has no room for sloppy thinking, and patients are not comforted by the phrase “nice effort.” But high standards and kindness are not enemies. A good teacher can be demanding without being cruel, precise without being pompous, and funny without turning the operating room into amateur night at a comedy club.
There are also hard experiences. Not every patient survives. Not every decision is obvious. Not every system works as designed. Trauma surgeons carry memories: the teenager after a crash, the elderly patient after a fall, the family waiting behind a curtain, the resident replaying a procedure in silence. In those moments, the old educational values return with new weight. Keep learning. Review the evidence. Talk to the team. Do not isolate yourself inside pride. Medicine is collaborative not because collaboration feels pleasant, but because the work is too important to be done alone.
After twenty years, the Yale System’s greatest gift may be this: it teaches that becoming a physician is not about proving you are the smartest person in the room. It is about becoming trustworthy in rooms where trust matters most. For a trauma surgeon, that lesson never expires.
Conclusion
A trauma surgeon reflecting on the Yale System 20 years later sees more than an unusual grading policy. The system is a philosophy of medical education built on maturity, independence, collaboration, research, feedback, and lifelong learning. Its no-rank culture can be uncomfortable for students trained to chase scores, but that discomfort can become transformative. It pushes future physicians to ask for help, learn with peers, study for patients rather than points, and carry humility into clinical practice.
In trauma surgery, those lessons matter every day. The trauma bay rewards teamwork over ego, preparation over performance, and honesty over image. The Yale System does not create perfect doctors. No system does. But at its best, it helps shape physicians who understand that knowledge is a responsibility, medicine is a team endeavor, and the real exam begins when a patient arrives needing your best work.